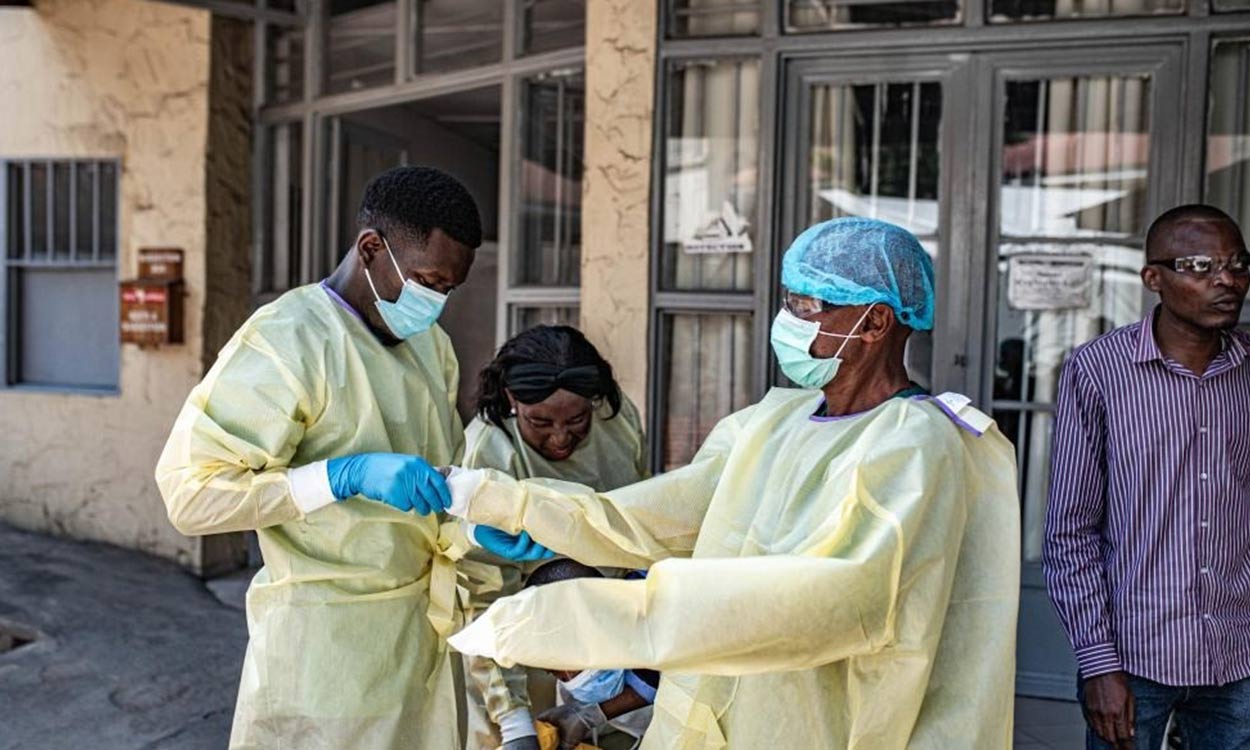
According to a situation report released Saturday by the DRC public health authorities, a total of 239 patients have recovered, while 628 confirmed patients are currently in isolation or hospitalization. Authorities have also identified 185 suspected cases.
The report said weekly confirmed cases have continued to rise, with epidemiological weeks 25 and 26 recording the highest levels so far, each exceeding 300 cases, indicating continued community transmission.
The report listed several major challenges, including community resistance to post-mortem sampling, insufficient capacity at Ebola treatment centers, especially in the eastern province of North Kivu, suboptimal contact tracing, delayed laboratory diagnosis, shortages of medical and infection-prevention supplies, insecurity and limited access in some affected areas.
The WHO said Thursday that a clinical trial had begun enrolling patients in the DRC to evaluate potential treatments for Ebola caused by the Bundibugyo virus, for which there is currently no approved vaccine or specific treatment.
Medical workers escort an Ebola patient to an Ebola treatment center in Mongbwalu, Ituri Province, the Democratic Republic of the Congo, June 20, 2026. (Xinhua)
In its latest Disease Outbreak News update, the WHO said that as of July 2, Uganda had reported 20 confirmed cases, including two deaths, as well as one probable fatal case.
The last confirmed case in Uganda was recorded on June 21. Separately, on June 24, French authorities notified the WHO of a laboratory-confirmed BVD infection in a medical doctor who had returned from the DRC.
In Uganda, the outbreak remains epidemiologically linked to transmission originating in the DRC, with evidence of both imported infections and secondary transmission among contacts and healthcare workers.
National authorities in the two affected countries, in collaboration with WHO and partners, are implementing an extensive set of response measures. A regional preparedness and prioritization framework continues to guide readiness activities across the African Region.
According to the WHO, BVD is a severe zoonotic illness, with fruit bats suspected as the natural reservoir, and it spreads to humans through contact with infected wildlife or bodily fluids of symptomatic individuals.
The incubation period is 2-21 days, with early non-specific symptoms like fever and fatigue often delaying diagnosis before progressing to gastrointestinal issues and hemorrhagic manifestations.
WHO’s current risk assessment, updated on June 6, rates the risk as very high in the DRC due to sustained transmission, and high in Uganda and neighboring countries due to cross-border mobility and historical outbreak links.
The risk for the rest of the African Region and globally is assessed as low, though sustained population movement and variable response capacities remain concerns for border areas.
Past outbreaks of this virus in 2007 and 2012 recorded case fatality rates of 30 percent and 50 percent, respectively.
Red Cross workers bury an Ebola victim at the Rwampara Cemetery, in Rwampara, Congo, Saturday, May 23, 2026.
According to the latest figures released by the Congolese government, the overall fatality rate stood at 30.6 percent. A total of 595 patients are currently in isolation or hospitalized, while 213 patients have recovered. The rate of contact follow-up across the three affected provinces stood at 82.7 percent.
The Africa Centers for Disease Control and Prevention (Africa CDC) Director-General Jean Kaseya warned Thursday that the ongoing outbreak remains “very serious”, as the current outbreak has recorded a particularly rapid increase in both cases and deaths compared with previous Ebola outbreaks in the DRC and the West African Ebola epidemic at the same stage.
DRC Health Minister Samuel-Roger Kamba called for accelerating clinical trials on monoclonal antibodies and the development of effective vaccines against Bundibugyo ebolavirus, for which no approved treatment currently exists.
The World Health Organization (WHO) said Thursday that a clinical trial had begun enrolling patients in the DRC to evaluate potential treatments for Bundibugyo virus disease.
According to the WHO, the trial will assess the monoclonal antibody MBP134 and the antiviral drug remdesivir, alone and in combination, to determine whether they can improve survival among patients diagnosed with Bundibugyo virus disease.
Health worker stands near displaced people waiting for the burial at Kigonze camp. Pic: Reuters
The case was identified through enhanced disease surveillance for Ebola, according to WHO. Ugandan health authorities notified WHO of the confirmed case on June 30. No new Ebola cases have been reported in the country since June 21.
Health authorities have informed WHO that they are monitoring all identified contacts of the Marburg case, but so far none have shown symptoms. WHO is supporting investigations to determine the source of exposure, assess the public health risk, and support community engagement.
According to the WHO website, Marburg virus disease (MVD), formerly known as Marburg haemorrhagic fever, is a severe, often fatal illness in humans. The average MVD case fatality rate is around 50 percent. Case fatality rates have varied from 24 percent to 88 percent in past outbreaks.
Early supportive care with rehydration, and symptomatic treatment improves survival. There are currently no approved vaccines or antiviral treatments for MVD, but a range of vaccines and drug therapies are under development.
The WHO said it continues to work with the Ugandan authorities to contain any potential spread and will provide further updates as the situation evolves.
“Today, the final contact of a person exposed to hantavirus on the cruise ship MV Hondius completed their quarantine period, tested negative and returned home. No further cases have been reported since May 25. We are therefore very pleased to say that WHO considers the outbreak of hantavirus over,” said WHO Director-General Tedros Adhanom Ghebreyesus during his opening remarks at the media briefing on Thursday.
The WHO was notified of the outbreak on May 2 by Britain’s International Health Regulations (IHR) National Focal Point. It involved a cluster of severe acute respiratory illness aboard the Dutch-flagged cruise ship.
A total of 13 cases were recorded, including three deaths. More than 650 contacts were identified and followed up by health authorities.
The outbreak response was supported by multiple countries in line with the International Health Regulations, including Argentina, Cabo Verde, Chile, the Netherlands, South Africa, Britain, and notably Spain, which demonstrated “incredible solidarity in supporting the safe disembarkation and repatriation of passengers and crew in Tenerife,” the director-general said.
Although the outbreak is now over, WHO will continue working with governments and partners to advance understanding of this outbreak and of hantavirus more generally.
WHO is coordinating a study involving 21 countries to understand how the disease develops, which will support the development of diagnostics, therapeutics, and vaccines for future outbreaks.
The World Health Organization (WHO) on Thursday declared the hantavirus outbreak linked to the cruise ship MV Hondius officially over, following the completion of quarantine for the final contact and no new cases reported for more than five weeks.
The findings, drawn from a nationally representative sample of over 20,000 women and men, show that 50% of men and 18% of women aged 15–49 drank alcohol in the last month, figures that point to a wide and persistent gender gap in drinking habits, even as frequency patterns look broadly similar across the two groups.
Frequency over volume
Most Rwandans who drink do so occasionally rather than heavily. Among those who consumed alcohol, 78% of women and 51% of men drank on just one to five days in the preceding month. Daily or near-daily drinking was reported by 7% of women and 15% of men.
When they did drink, men were more likely than women to have several drinks in one sitting. Among male drinkers, 32% had no more than one drink per session, compared with 48% of female drinkers. At the other end of the scale, 12% of men and 14% of women who drank consumed six or more drinks on a typical drinking day.
Drinking rises sharply with age
The survey shows a clear age gradient for both sexes. Among women, alcohol consumption climbs from 7.5% among 15–19-year-olds to 28.9% among those aged 45–49. Among men, the increase is steeper and comes earlier: from 22.2% among teenagers to over 60% by their early 30s, peaking at 64.8% among men aged 40–44.
Regional and economic divides
Alcohol use varies markedly by province, and the pattern looks different for men and women.
Among women, Northern Province (26.1%) and Southern Province (25.6%) recorded the highest rates of alcohol consumption, more than double the 10.5% recorded in the City of Kigali, the lowest of any province. Western and Eastern Provinces fell in between, at 13.3% and 15.6% respectively.
Among men, the geography shifts, though Northern Province again tops the list, at 59.4%. It is followed by Southern Province (54.1%), Eastern Province (45.7%), Kigali (49.7%), and Western Province, which recorded the lowest male consumption at 45.3%. Notably, Kigali records the lowest alcohol use among women but sits roughly in the middle among men, while Western Province is consistently the lowest- or near-lowest-consuming province for both sexes.
The rural-urban split tells a smaller but still notable story. Rural women were more likely to drink than urban women (20.5% versus 12.7%), while the gap between rural and urban men was minimal (50.9% versus 48.8%), suggesting alcohol use among men is fairly evenly distributed regardless of setting, whereas for women, urban residence appears to correlate with lower consumption, mirroring the wealth pattern seen nationally.
Wealth shapes drinking for both sexes, though the pattern is clearer among women. Women in the poorest wealth quintile were roughly twice as likely to have consumed alcohol in the last month (24.4%) as those in the wealthiest quintile (11.8%). Among men, consumption was also highest in the poorest quintile (59.3%) and lowest among the wealthiest (41.7%), though the decline was less consistent in between, dipping to 49.4–49.5% in the middle quintiles before falling further at the top.
Education shows a similar gradient for women, alcohol use falls steadily from 24.9% among those with no education to 11.5% among those with more than secondary education. Among men, the pattern is less consistent: consumption drops from 62.5% (no education) to 41.3% (secondary), then rises again to 50.3% among the most educated group.
A different picture from tobacco use
The RDHS report notes that alcohol consumption is far more widespread than tobacco use in Rwanda, where just 1% of women and 6% of men aged 15–49 currently smoke or use tobacco products. Tobacco use among men has declined slightly since the previous survey, from 7% in 2019–20 to 6% in 2025.
Unlike tobacco, which is most heavily concentrated among older, less educated and lower-income men, alcohol consumption follows a somewhat similar socioeconomic gradient among women, while showing a less consistent pattern among men.
The report cautions that heavy alcohol intake carries significant health risks, including increased risk of alcoholism, malnutrition, chronic pancreatitis and liver disease, as well as risks to maternal and child health when consumed during pregnancy.
The 2025 RDHS was implemented by the National Institute of Statistics of Rwanda (NISR) in collaboration with Rwanda’s Ministry of Health.
Half of Rwandan men and nearly one in five women aged 15–49 consumed alcohol in the month before they were interviewed for the 2025 Rwanda Demographic and Health Survey (RDHS), according to the survey’s final report released on June 30, 2026.
The figures showed that 192 patients had recovered, while 609 others were receiving treatment or under care.
The outbreak remains concentrated in the eastern provinces of Ituri, North Kivu and South Kivu, where surveillance, medical care and response operations are continuing.
The government said response capacity is being strengthened through the deployment of vehicles and ambulances, the supply of medicines and personal protective equipment, and intensified communication and community mobilization efforts.
The DRC declared the outbreak in mid-May. Health authorities and international partners have repeatedly warned that insecurity, population movement, pressure on health facilities and incomplete contact tracing continue to complicate the response.
The outbreak remains concentrated in the eastern provinces of Ituri, North Kivu and South Kivu, where surveillance, medical care and response operations are continuing.
The discovery, highlighted in a recent study reported by ScienceDaily, shows that these specialized brain cells act like an internal “attention control system,” allowing the brain to concentrate on important information while ignoring irrelevant stimuli in the environment.
Researchers found that when these neurons were temporarily switched off in laboratory experiments involving mice, the animals became significantly more easily distracted.
Their attention shifted rapidly between stimuli, resembling attention difficulties seen in conditions such as ADHD. However, once the neurons were reactivated, normal focus and attention control were restored.
The findings suggest that this ancient brain circuit is essential for maintaining stable attention and could represent a fundamental mechanism that has been preserved through evolution to support survival.
Scientists believe the discovery could open new pathways for understanding attention-related disorders, including ADHD and other cognitive conditions where focus and information filtering are disrupted.
By targeting this neural system, future treatments may be able to improve attention control without broadly affecting other brain functions.
The study adds to growing evidence that even small and previously overlooked groups of neurons can play a major role in shaping human cognition, behavior, and mental performance.
As research continues, scientists hope to better understand how this attention-filtering system works in the human brain and how it might be used to develop more precise neurological therapies in the future.
Scientists have identified ancient brain cells that help filter out distractions.
The figure, drawn from HIV serology testing of nearly 13,000 women and men, confirms a steady decline in the country’s epidemic: prevalence held at 3.0% from 2005 through 2014–15, before easing to 2.7% in the 2019–20 RDHS and now 2.2% in 2025. The report describes the drop between 2019–20 and 2025 as statistically significant.
But the national average masks wide disparities that the survey’s authors say still call for targeted intervention, by sex, by geography, and by wealth and education.
A persistent gender gap
Women continue to bear a heavier burden of HIV. The survey found prevalence among women aged 15–49 at 2.8%, nearly double the 1.5% recorded among men.
This gap persists even though women account for a slight majority of Rwanda’s population. The 2022 Rwanda Population and Housing Census recorded 13,246,394 people, comprising 6,817,067 females (51.5%) and 6,429,326 males (48.5%).
Compared with the 2019–20 survey, HIV prevalence among women declined from 3.5% to 2.8%, a statistically significant reduction, while prevalence among men decreased slightly from 1.7% to 1.5%, a change that was not statistically significant.
The gap widens further with age. Among women aged 45–49, prevalence reaches 7.8%, compared with 3.5% among men in the same age bracket, and 4.3% among men aged 50–59. Prevalence generally climbs with age for both sexes, from under 1% among teenagers to its peak in the 40s and 50s.
Marital and relationship status also shapes risk. Widowed respondents have the highest prevalence of any group at 10.9%, followed by those who are divorced or separated at 7.3%. Women in polygynous unions show notably higher prevalence (6.5%) than those in non-polygynous unions (2.3%).
Male circumcision continues to show a protective association: HIV prevalence is 1.2% among circumcised men, compared with 2.5% among men who are not circumcised or do not know their status.
Cities carry a heavier burden than the countryside
Geography remains one of the sharpest dividing lines in Rwanda’s HIV epidemic. Prevalence in urban areas stands at 3.3%, almost double the 1.7% recorded in rural areas, a pattern consistent with previous rounds of the survey and with the country’s broader urban–rural health disparities.
The provincial breakdown tells a similar story. The City of Kigali has the highest prevalence in the country at 3.7%, more than triple the 1.0% recorded in the Northern Province, which posts the lowest rate nationally. Southern Province (2.3%), Western Province (2.2%), and Eastern Province (2.0%) fall in between.
Education levels also showed clear differences in HIV prevalence. The survey found HIV prevalence was highest among people with no formal education (4.9%), followed by those with primary education (2.4%), secondary education (1.6%), and more than secondary education (0.9%). By household wealth, the poorest quintile recorded the highest prevalence (3.3%), though the pattern across the remaining wealth groups was less consistent.
Testing coverage remains high
The survey’s underlying data quality is bolstered by near-universal participation: 99% of eligible women and 97% of eligible men consented to HIV testing and provided a blood sample for the survey’s testing algorithm, carried out through Rwanda’s National Reference Laboratory. Fewer than 1% of eligible respondents refused testing outright.
Rwanda has been widely recognized as a regional leader in HIV control, having met the UNAIDS 95–95–95 targets for diagnosis, treatment, and viral suppression ahead of the 2025 deadline.
With prevalence now confirmed at 2.2% nationally, the survey gives policymakers a clearer map of where continued gains are still to be made, particularly among older women, urban populations, and the City of Kigali, building on a strategy that has already brought the country this far.
Meanwhile, the HIV findings sit alongside a wider set of health gains captured in the 2025 RDHS. Fertility has continued its long decline, with the total fertility rate now at 3.7 children per woman. Child survival has also improved: under-5 mortality has fallen to 36 deaths per 1,000 live births, down from 45 in the previous survey, while infant and neonatal mortality have declined in tandem.
Chronic child malnutrition is down too, 27% of children under five are stunted, compared with 51% two decades ago, and contraceptive use among married women has climbed to 69%, with the government sector remaining the primary source of family planning services nationwide.
Women continue to bear a heavier burden of HIV. The survey found prevalence among women aged 15–49 at 2.8%, nearly double the 1.5% recorded among men.
According to the figures released Tuesday by the government, 609 patients were in isolation or hospitalized, while 189 people had recovered. The contact follow-up rate in the three affected provinces reached 82.7 percent.
The outbreak, caused by the Bundibugyo virus, remains “active” in the DRC, with transmission continuing in several hotspot areas, the World Health Organization (WHO) said in its report released on Tuesday.
Important operational gains had been made, including better contact follow-up, expanded decentralized laboratory capacity, increased treatment capacity and strengthened cross-border coordination, the WHO said.
However, the WHO warned that the response “remained below the level required to interrupt transmission rapidly,” citing the continued increase in cases and deaths, near-saturation of treatment facilities and insufficient infection prevention and control readiness in health facilities as signs that a stronger operational surge was urgently needed.
Beyond the health emergency, the outbreak is also raising alarms over its economic and social impact. A new assessment by the United Nations Development Programme (UNDP) warned on Tuesday that the Ebola crisis could push 985,000 more people into poverty in the DRC, with women disproportionately affected by the economic and health fallout.
The UNDP also warned that the crisis risks eliminating tens of thousands of jobs, disrupting education and healthcare services, and costing African economies up to 3.6 billion U.S. dollars if broader regional and global shocks intensify.
Even under a baseline scenario in which the virus is contained in the DRC and Uganda, the DRC could face real GDP losses of more than 1 billion dollars and the loss of 55,000 jobs, according to the UNDP assessment.
Meanwhile, the Africa Centers for Disease Control and Prevention (Africa CDC) on Tuesday called for urgent funding to support clinical trials for candidate therapeutics against Bundibugyo Ebola virus.
It said trials evaluating candidate therapeutics were being launched this week in Bunia, capital of DRC’s Ituri Province, epicenter of the outbreak, marking an important step in the response to a strain for which there is currently no licensed vaccine or therapy.
Africa CDC said financing for vaccine trials was largely in place, but a funding gap remained for therapeutic trials, which only secured 10 million dollars. It appealed for immediate additional financing, including 16 million dollars for a post-exposure prophylaxis study among exposed contacts and another 2 million to 3 million dollars to strengthen contact tracing needed for the trial.
“We have the science. We now need the funding to use it. Clinical trials must start this week, and every day of delay costs lives we could save,” Africa CDC Director General Jean Kaseya said in a statement on Tuesday.
The DRC declared the outbreak in mid-May. Health authorities and international partners have repeatedly warned that insecurity, population movement, pressure on health facilities and incomplete contact tracing continue to complicate the response.
Medical workers escort an Ebola patient to an Ebola treatment center in Mongbwalu, Ituri Province, the Democratic Republic of the Congo, June 20, 2026. (Xinhua)