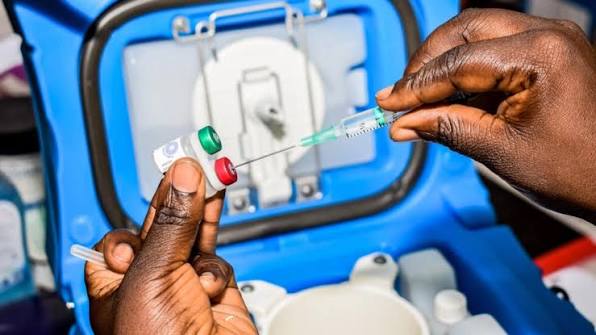
Born in 2000, Hategekimana says he was diagnosed with polio in 2001, despite having received a polio vaccine during infancy. The circumstances surrounding his infection are unclear.
The effects of his condition remain part of his daily life. He says walking long distances, particularly uphill, is difficult because he becomes tired quickly. His mobility is also limited by the cost of transport, sometimes restricting how far he can travel when he cannot afford a motorcycle taxi. He also experiences breathing difficulties and bone pain, challenges he has had to manage while pursuing his education.
Polio is a highly infectious disease caused by a virus that attacks the nervous system and can cause permanent paralysis. According to the World Health Organization (WHO), “one in 200 infections leads to irreversible paralysis.” Among people who develop paralysis, 5–10% die when the muscles responsible for breathing become immobilised.
The disease mainly affects children under five, although unvaccinated people of any age can contract it. There is no cure for polio, but vaccination can prevent the disease.
Hategekimana’s experience was not limited to physical difficulties. During primary school, he says he was bullied because of his disability, an experience that formed part of his childhood.
Despite these challenges, Hategekimana continued with his education. He is now in his fourth year at Mount Kigali University, pursuing a Bachelor of Arts in Mass Media and Communications, a programme that is bringing him closer to a career he has long admired.
Hategekimana says his interest in journalism developed from listening to journalists on the radio.
“I hope to become a journalist and a presenter so I can be the voice for people with disabilities,” he said.
He hopes to become a journalist and presenter, with a particular interest in telling stories that bring attention to the experiences of people with disabilities.
He has already begun putting that interest into practice through his YouTube channel, Twese Turashoboye TV. The channel features interviews in Kinyarwanda, giving him a platform to speak with people and share their different experiences.
His education has also received support from Rulindo District officials, which he says has helped him continue his studies by supporting his tuition costs.
Hategekimana says his experiences have strengthened his desire to speak for people whose stories are often overlooked. He believes people living with disabilities deserve understanding, support and opportunities to participate fully in society.
He urges parents to ensure their children receive all recommended doses of the polio vaccine, stressing the importance of vaccination in protecting children against the disease.
Born in 2000, Olivier Hategekimana says he was diagnosed with polio in 2001, despite having received a polio vaccine during infancy. The circumstances surrounding his infection are unclear.
The Rwanda Climate and Health Vulnerability and Adaptation Assessment 2025, published by the Ministry of Health on October 23, 2026, maps areas where climate hazards could intensify existing health challenges and examines how prepared the country’s health system is to respond.
The assessment identifies significant differences in climate-health risks across Rwanda’s districts. In the western highlands, Rusizi, Nyamasheke, Rubavu and Ngororero emerge as high-risk hotspots, with Ngororero recording the highest overall risk in the country. Gakenke is also identified among the high-risk districts. By contrast, Kicukiro, in Kigali City, and Rwamagana, in the Eastern Province, record the lowest overall climate-health risk.
The assessment identifies a medium-risk belt across parts of the north, including Musanze and Burera, while risk is generally lower across much of the east and Kigali. It also identifies a low-impact corridor across the south and southeast, including Nyamagabe, Nyaruguru, Huye and Gisagara, with smaller low-impact pockets in Kicukiro, Rwamagana and Nyabihu.
In Kigali, urban areas such as Gasabo are also identified as vulnerable to heat and flooding, highlighting the growing importance of climate-resilient urban health planning.
The report warns that these hazards are not only environmental concerns. They can disrupt access to healthcare, damage health infrastructure, affect water and sanitation services and increase the burden of diseases that are sensitive to climate conditions.
Climate risks and disease burden
The assessment examines 17 climate-sensitive diseases using district-level monthly health data covering January 2019 to December 2024.
Among the health concerns highlighted are malaria, schistosomiasis, diarrhoeal diseases, intestinal parasites, respiratory illnesses, asthma, chronic obstructive pulmonary disease, cardiovascular conditions and malnutrition.
The report identifies seasonal patterns in several of these diseases, with some increases coinciding with rainy periods and changing climate conditions.
Transmission of waterborne diseases is closely linked to rainfall and environmental conditions. Notably, the report reveals that schistosomiasis is sharply concentrated along the western lakeshore, with Nyamasheke, Rubavu, Rutsiro, and Rusizi forming an intense regional cluster around the Lake Kivu basin where water-contact sites and snail habitats drive local transmission.
Malaria remains a particular concern in areas where environmental conditions can support mosquito breeding. Flooding and changes in rainfall can also affect water quality and sanitation, increasing the risk of diarrhoeal diseases and other water-related infections.
The assessment cautions that observed relationships between climate conditions and disease patterns should not automatically be interpreted as proof of direct causation. Other factors, including access to healthcare, population movement, sanitation and disease-control interventions, also influence health outcomes.
Vulnerable communities face greater exposure
The effects of climate change are not expected to be evenly distributed across the population.
The assessment identifies pregnant and postpartum women, children under five, adolescents, older people, persons with disabilities, displaced populations and low-income communities as groups that may face greater risks.
Disruption to healthcare services during extreme weather events can make it harder for pregnant women to access antenatal care, skilled delivery services and emergency obstetric care. Children are also vulnerable to the effects of unsafe water, poor sanitation, malnutrition and climate-sensitive infections.
The report records a decline in Rwanda’s maternal mortality ratio from 197 deaths per 100,000 live births in 2019 to 145 in 2024. However, it also identifies seasonal variation, with a reported peak of 213 in February.
It further notes that deliveries among girls under 20 increased from 5.7 per cent in 2021 to 6.6 per cent in 2024, with higher proportions recorded in some eastern districts.
Gender-based violence also features in the assessment. Reported cases show seasonal increases between August and October, although the report cautions that changes in reporting and access to services may influence the figures.
The assessment estimates that approximately 137,000 forcibly displaced people are among the populations whose vulnerability and access to essential services require consideration in climate adaptation planning.
Poverty is another underlying factor. The report cites approximately 3.6 million people, or 27.4 per cent of the population, living in poverty in 2024, potentially limiting their ability to prepare for and recover from climate-related shocks.
Health facilities face preparedness gaps
Beyond the risks facing communities, the assessment raises concerns about the ability of health facilities to withstand and respond to climate-related emergencies.
An assessment of 10 district hospitals across Rwanda’s five provinces examined infrastructure, water, sanitation, energy and workforce preparedness. The study also drew on qualitative input from 170 health-sector stakeholders.
The findings point to uneven readiness across key areas. Workforce readiness was assessed at 42 per cent, compared with 69 per cent for water, sanitation and hygiene, and 64 per cent for energy.
The report identifies important gaps in human-resource planning. Only 20 per cent of assessed facilities had contingency plans for mobilising staff, while 30 per cent had shift-relay systems. Just 10 per cent reported post-event recovery support for staff, and the same proportion involved health workers in climate adaptation planning.
Water and sanitation systems also require greater attention. Only 30 per cent of facilities had updated risk assessments for sanitation infrastructure, while monitoring of stormwater and sewer overflows remained limited.
Although all assessed facilities had emergency backup generators and maintenance arrangements, only 10 per cent assessed whether their renewable energy capacity was sufficient.
The report also finds that facilities are generally better prepared for floods and storms than for drought and extreme heat. It highlights the absence of facility-level climate-health early-warning systems as another important weakness.
In a separate survey of 93 respondents, heavy rainfall was the most frequently reported hazard affecting facilities, cited by 73 per cent. Flooding followed at 64 per cent, while strong winds and storms were reported by 36 per cent, lightning by 33 per cent and landslides by 30 per cent.
Drought and extreme heat were also reported, at 24 per cent and 21 per cent respectively.
Respondents associated these hazards with health problems including malaria, respiratory infections, diarrhoea and cholera, and malnutrition.
Rising temperatures expected
The assessment’s climate projections indicate that Rwanda will continue to experience rising temperatures over the coming decades, although the scale of warming will depend on future global emissions.
Compared with the 1985–2014 baseline, projected increases in mean annual temperature under the lower-emissions SSP1-2.6 scenario are approximately 0.93°C by 2030, 1.38°C by 2055 and 1.43°C by 2080.
Under the higher-emissions SSP5-8.5 scenario, the projected increase reaches approximately 1.01°C by 2030, 2.36°C by 2055 and 4.08°C by 2080.
The report notes greater uncertainty around future rainfall projections, making rainfall variability and the frequency of heavy precipitation important considerations for planning.
Rising temperatures could increase heat-related health risks, while changes in rainfall patterns may affect the distribution of disease vectors, water availability and the frequency of flooding.
Call for stronger climate-health planning
The assessment calls for climate considerations to be integrated more systematically into Rwanda’s health planning, disease surveillance and emergency preparedness.
Among its recommendations is the development of climate-health early-warning systems that connect meteorological information with health surveillance data. Such systems could help authorities anticipate periods of increased disease risk and prepare health services before emergencies occur.
The report also recommends strengthening preparedness for seasonal increases in malaria, schistosomiasis, diarrhoeal diseases and respiratory illnesses, alongside improving the capacity of health facilities to maintain essential services during extreme weather events.
It calls for climate-resilient infrastructure, improved water and sanitation systems, reliable energy supplies, better workforce planning and training for health professionals.
Integrating climate-related information into the Health Management Information System would also help authorities monitor emerging patterns and support evidence-based decisions.
The assessment further recommends targeted adaptation measures across five geographical zones, recognising that districts face different combinations of climate hazards and health vulnerabilities.
The assessment was led by the Ministry of Health with primary support from the Agence Française de Développement (AFD), the Clinton Health Access Initiative (CHAI), UNICEF, and UNFPA.
A flooded wetland at Masaka in Kicukiro District in April 2022. The Rwanda Climate and Health Vulnerability and Adaptation Assessment 2025, published by the Ministry of Health on October 23, 2026, maps areas where climate hazards could intensify existing health challenges and examines how prepared the country’s health system is to respond.
The study marks a critical step in the development of the compound known as MMV371 and is the first Phase 1 trial of a malaria LAI to be conducted in Africa.
Provided that they prove to be safe and effective, LAIs could become an important addition to the malaria prevention toolbox, complementing existing interventions such as vector control measures, vaccines and preventive medicines.
Despite significant progress against malaria since the turn of the century, the disease remains a major public health challenge.
According to the World Health Organization, in 2024, malaria caused over 280 million cases and 600,000 deaths, 95% of which occurred in Africa.
The continued emergence of antimalarial drug resistance, changing disease patterns driven by climate change-related extreme weather events and fragile health systems highlight the need for sustained investment in R&D and continued innovation, coupled with greater access to malaria prevention and treatment tools.
Given these challenges, MMV is working with partners to develop the first LAI designed to provide extended protection against malaria.
The Phase 1b study builds on earlier clinical research conducted in the United Kingdom, which found that MMV371 was well tolerated in healthy adults and showed the potential to provide protection for approximately 3 months.
This next phase will evaluate its safety and tolerability in Rwandan adults and adolescents, explore its efficacy, and understand how the body absorbs and processes the compound.
“To eliminate malaria, we will need not only wider access to today’s tools but also the next generation of prevention technologies,” said Dr. Martin Fitchet, Chief Executive Officer of MMV. “
Long-acting injectables have the potential to redefine how malaria prevention is delivered, providing sustained protection from a single administration and expanding the options available to communities at risk.”
Partnerships for malaria elimination
Partnerships are critical to the development of new malaria interventions. MMV has a strong track record of working with partners across industry, government and academia to bring new medicines to those who need them.
The collaboration with Rinda Ubuzima builds on this approach, reflecting a shared commitment to advancing innovation through locally led research, while strengthening scientific research capacity and generating the evidence needed to develop the next generation of malaria tools.
“Conducting this study in Rwanda demonstrates that partnerships such as this are essential to ensuring that African researchers and institutions are active contributors to the development of solutions for the communities and countries that need them most,” said Marie Michele Umulisa, Executive Director of Rinda Ubuzima. “We are proud to contribute to research that could help shape the future of malaria prevention while strengthening locally led scientific innovation.”
As countries work towards ending malaria, collaborative efforts such as this clinical trial are helping to pave the way for new preventive approaches and expand the range of tools available to protect at-risk communities.
The study also reflects a broader shift towards conducting increasingly sophisticated early-stage clinical research in malaria-endemic countries and ensuring that the development of medicines is informed by the communities they are intended to serve earlier in the R&D process.
Malaria remains a major public health challenge, particularly in Africa, where 95% of the approximately 600,000 deaths recorded worldwide in 2024 occurred.
The discovery offers new insights into how human eyesight develops before birth and could eventually contribute to research into treatments for conditions that cause vision loss.
The research, published in the Proceedings of the National Academy of Sciences (PNAS), examined the foveola, a small area located at the centre of the retina that enables people to see fine details, read and recognise faces.
Led by Associate Professor Robert J. Johnston Jr., the researchers used laboratory-grown miniature human retinal tissues, called organoids, to study how cells in the eye develop over time.
Their observations revealed that during early fetal development, some cells that initially detect blue light may change into cells responsible for detecting red and green light.
The transformation is influenced by retinoic acid, a substance derived from vitamin A, and thyroid hormones, which play important roles in regulating growth and development.
The researchers found that retinoic acid helps organise the developing retina by restricting the formation of blue-light-sensitive cells in its central region.
Meanwhile, thyroid hormones appear to trigger some of the remaining blue-sensitive cells to develop into red- and green-sensitive cells.
The discovery challenges a long-standing scientific explanation, which suggested that blue-sensitive cells simply moved away from the centre of the developing retina without changing their function.
Instead, the new findings indicate that some of these cells may undergo a transformation, adopting different roles as the eye develops.
“This is a key step toward understanding the inner workings of the center of the retina, a critical part of the eye and the first to fail in people with macular degeneration,” Johnston said.
The findings could help advance future research into treatments for vision-threatening conditions, including macular degeneration and glaucoma.
Scientists hope that further improvements in laboratory-grown retinal tissues could eventually make it possible to develop specialised light-sensitive cells capable of replacing those damaged by eye diseases.
However, the technology is still at an experimental stage, and further studies will be necessary to determine whether it can safely and effectively restore vision in patients.
The research provides new insight into the biological processes that enable the human eye to develop the ability to distinguish fine details.
Researchers have discovered how vitamin A and thyroid hormones contribute to the development of sharp human vision.
The findings, published in The Lancet Regional Health Americas and presented at the Annual Meeting of the European Association for the Study of Diabetes (EASD), suggest that lifestyle changes could offer an effective approach to managing early-onset Type 2 diabetes.
The research was conducted by scientists led by Professor Kaberi Dasgupta of McGill University in Canada and Professor Thomas Yates of the University of Leicester in the United Kingdom.
The clinical trial involved 96 adults aged between 18 and 45 who had Type 2 diabetes and obesity but were not using insulin.
Participants were recruited at research centres in the United Kingdom and Canada.
Of the 96 participants, 50 were assigned to an intensive lifestyle programme, while 46 continued receiving standard medical care.
Those in the lifestyle group followed a diet providing between 800 and 900 calories daily, alongside supervised aerobic and resistance exercises twice a week and an additional independent exercise session.
After 12 weeks, participants moved to a diet designed to maintain their weight loss while continuing physical activity.
After 24 weeks, 27 of the 50 participants in the intensive programme had achieved remission, representing 54%.
In comparison, only two of the 46 participants receiving standard care achieved remission, equivalent to approximately 4%.
Researchers also recorded greater weight loss among participants following the intensive programme.
Their average body weight decreased by 8.4 kilogrammes over six months, compared with 1.2 kilogrammes among those receiving standard care.
The programme also focused on preserving muscle mass through resistance training while reducing body fat.
However, the intensive approach was associated with more side effects.
Forty-three participants in the intervention group reported at least one adverse event, compared with six in the standard-care group. Common problems included constipation, headaches, dizziness and fatigue. No severe adverse events were reported.
Researchers emphasised that remission does not necessarily mean diabetes has been permanently cured.
It refers to blood sugar levels falling below the diagnostic threshold without glucose-lowering medication for a specified period.
They said longer-term studies are needed to establish whether participants can maintain remission and weight loss over time.
The findings could offer new insights into treating early-onset Type 2 diabetes, which is associated with a higher risk of developing complications earlier in life.
A new study has found that combining a low-calorie diet with regular exercise can help young adults with Type 2 diabetes achieve remission.
The International Air Transport Association (IATA) and Airlines for America made the appeal in separate letters to the US Centers for Disease Control and Prevention (CDC).
The rules, scheduled to take effect on November 3, require passengers and crew members on international flights to the United States to sign a digital or paper declaration confirming they have not been in the Democratic Republic of Congo (DRC) during the preceding 21 days.
IATA, which represents more than 370 airlines in over 130 countries, said airlines had insufficient time to adapt their systems and procedures to the requirement.
“It is unreasonable for the U.S. government to require all airlines serving the U.S. market to modify their procedures to accommodate the collection of attestations from each individual (passenger and crew) flying to the United States in less than two weeks,” the association said in its letter, as quoted by Reuters.
Airlines for America, which represents major US carriers including United Airlines, American Airlines, Southwest Airlines and Delta Air Lines, also described the plan as difficult to implement within the available timeframe.
The group said airlines would need to adjust check-in systems, introduce digital signatures, update procedures at airports and train staff to enforce the requirement.
It called on the CDC to consider a more measured response and urged exemptions for crew members, US military personnel and passengers travelling in aircraft jump seats.
The industry group also cited figures showing that US Customs and Border Protection screened approximately 130 million air passengers in 2025, fewer than 25,000 of whom had a connection to the DRC.
IATA questioned why the declaration requirement applies to air travel but not to maritime and land transportation but the CDC has also not publicly responded to the airline groups’ appeal.
The new requirement comes amid a major outbreak of Bundibugyo virus disease, a form of Ebola, centred in the DRC and with confirmed imported cases reported in other countries.
According to the US Centers for Disease Control and Prevention (CDC), the Bundibugyo Ebola outbreak had reached 10,172 confirmed cases and 4,932 confirmed deaths across five affected countries as of October 26, 2026.
The Democratic Republic of Congo accounted for 10,141 cases and 4,928 deaths, while Kenya had reported nine cases, including two deaths.
Uganda had recorded 20 confirmed cases and two deaths, Nigeria one confirmed case, and France one confirmed case. The outbreak has spread across the five countries since it was declared in the DRC on May 15, 2026.
The outbreak has prompted authorities to strengthen surveillance, contact tracing and preparedness measures across borders.
The CDC says the 21-day declaration requirement is intended to reduce the risk of Ebola entering the United States through air travel. The period corresponds to the maximum incubation period for Ebola disease.
Under the order, airlines must ensure that covered travellers complete the declaration before boarding. Those who fail to provide it may not be allowed to board unless they qualify for an exemption.
The requirement applies to US citizens and other eligible travellers departing from foreign countries, including those connecting through the United States.
While the airline groups have raised concerns about implementation costs and operational difficulties, the dispute highlights the challenge of introducing emergency public health measures across an international aviation network.
The WHO has advised against restrictions on travel to or trade with affected countries, while emphasising the importance of cross-border cooperation, surveillance and preparedness as the outbreak continues.
The International Air Transport Association (IATA), which represents more than 370 airlines worldwide, has warned that carriers have insufficient time to adjust their systems and procedures to comply with new US Ebola-related travel declaration requirements.
The announcement was made on October 27, 2026, when King Faisal Hospital hosted a team of transplant surgery specialists from Türkiye’s Acıbadem Healthcare Group.
The visit aims to strengthen cooperation towards introducing liver transplantation in Rwanda, building on kidney transplant services launched at the hospital in May 2023.
King Faisal Hospital’s Chief Medical Officer, Dr. Augustin Sendegeya, said the number of patients requiring liver transplants in Rwanda is increasing, while delays in accessing the procedure can put their lives at risk.
He explained that transplantation may be the only life-saving option when the liver is severely damaged and can no longer perform its essential functions.
Dr. Sendegeya added that liver transplants are expensive abroad, making the introduction of the service in Rwanda an important step towards reducing the financial and logistical challenges faced by patients.
“We have welcomed specialists from Türkiye’s Acıbadem Healthcare Group. We will discuss how to introduce new liver transplant services. We will also collaborate on research and train doctors in kidney and liver transplantation,” he said.
Dr. Sendegeya noted that Rwanda has already made progress in kidney transplantation, with about 115 patients having received the procedure at King Faisal Hospital.
Prof. Hamdi Karakayali, a transplant specialist at Acıbadem Healthcare Group, said diseases affecting the kidneys and liver are increasing worldwide, creating a need to expand treatment capacity.
He described kidney transplantation as a highly effective treatment, noting that success rates can reach 99% when procedures are performed by experienced specialists.
Patients with damaged kidneys can also undergo haemodialysis, a procedure that uses a machine to filter waste and excess fluid from the blood, performing some of the functions of the kidneys.
However, he said, liver failure presents a greater challenge because no machine can fully replace the liver’s functions when the organ is severely damaged.
“Liver diseases are very serious and difficult to treat. When the liver is severely damaged, transplantation may be necessary. Liver transplants have a success rate of more than 90%,” Karakayali said.
He said that during his 33 years in transplant medicine, he had participated in kidney transplants for approximately 3,500 patients and liver transplants for another 2,500.
Karakayali said one of the most rewarding aspects of his work is seeing patients recover and resume their lives, particularly children.
“It makes me happy to see the people I have treated recover, especially children. It is rewarding to treat a child who survives, goes to school and later returns as an adult with a family of their own,” he said.
Organ donation remains a major challenge
Karakayali said the availability of people willing to donate organs remains one of the biggest challenges facing transplantation programmes worldwide.
He explained that organ donation requires more than medical expertise, stressing the importance of following applicable laws and regulations to protect the rights and safety of both donors and recipients.
Türkiye has made progress in living-donor liver transplantation, he said, with approximately 80% of the 1,400 liver transplants performed there involving organs donated by living people.
Living donors can donate part of their liver because the organ has the ability to regenerate.
Liver transplants can also use organs donated by deceased people, subject to the relevant legal and medical requirements.
Karakayali said that although both options are available, securing enough donor organs remains a major challenge.
King Faisal Hospital’s Chief Medical Officer, Dr. Augustin Sendegeya, said the number of patients requiring liver transplants in Rwanda is increasing.Prof. Hamdi Karakayalı, MD is a kidney transplant center specialist at Acibadem Atakent Hospital in Istanbul.The representative of Acıbadem Healthcare Group in Rwanda and other African countries said patients seeking organ transplants in Türkiye receive assistance.Transplant specialists from Türkiye are working with Rwandan counterparts to introduce liver transplant services in the country.
The outbreak has claimed 4,887 lives across eight provinces since it was declared in mid-May, making it the largest Ebola outbreak in the country’s history and the second-largest recorded globally.
More than 2,700 children have been infected, according to Save the Children, highlighting the growing impact of the outbreak on vulnerable populations.
Greg Ramm, the organisation’s director in the DRC, described the milestone as a “stark reminder of the scale of this crisis”.
“Behind this milestone are thousands of families facing unimaginable fear and uncertainty, and children are bearing some of the heaviest consequences,” Ramm said.
He added that the outbreak was unfolding in communities already affected by conflict, displacement and food insecurity, making it increasingly difficult for families to access medical services.
“Families are struggling to access health care, health facilities are under immense pressure, and many communities lack the resources needed to prevent transmission and keep children safe,” he said.
The outbreak is caused by the Bundibugyo strain of Ebola, a relatively rare variant for which no approved vaccine is currently available, according to the report.
Difficulties in detecting the virus during the early stages of the outbreak have also complicated efforts to contain its spread.
Attacks on health workers hamper response
Efforts to control the outbreak have also been undermined by violence against health workers.
Last week, a nurse was killed and another health worker seriously injured while responding to an Ebola alert in Tshopo province in the Democratic Republic of Congo according to the World Health Organization (WHO).
WHO Director-General Tedros Adhanom Ghebreyesus condemned the attack, stressing that health workers must be able to carry out their duties safely.
“Everyone working to protect communities from this deadly disease must be able to work in dignity and safety,” he said in a post on X.
WHO Regional Director for Africa Mohamed Janabi also called for the protection of those responding to the outbreak, warning against the consequences of misinformation and fear.
“Those responding to the Ebola outbreak must be protected,” Janabi said.
The insecurity has added to the challenges facing response teams, particularly in areas where mistrust and misinformation discourage residents from reporting symptoms or seeking treatment.
The outbreak has also placed pressure on already strained healthcare facilities, while conflict and displacement have made it more difficult for response teams to reach affected communities.
Regional spread raises concern
The outbreak has extended beyond the DRC, with Kenya and Nigeria reporting cases linked to the ongoing crisis. Health authorities are intensifying surveillance and coordination as they seek to prevent further transmission.
Africa Centres for Disease Control and Prevention (Africa CDC) Director-General Jean Kaseya has called for a stronger and faster continental response.
“Ebola is crossing borders,” Kaseya said. “We have the expertise and the capacity on this continent. We must mobilise them together to stop this outbreak and save lives.”
Kenya has reported deaths linked to the outbreak, while almost 100 close contacts of other cases remained in quarantine, according to ABC News.
Uganda, which shares a border with the DRC, has introduced restrictions on non-essential travel to and from the neighbouring country. Returning citizens are also expected to undergo a 21-day quarantine under the measures.
The developments have renewed concerns about cross-border transmission and the need for countries to strengthen screening, contact tracing and emergency preparedness.
A healthcare worker decontaminates his colleague after he entered the house of an old woman, suspected of dying of Ebola, in the eastern Congolese town of Beni in the Democratic Republic of Congo, Oct. 8, 2019. Zohra Bensemra/Reuters
The committees will review scientific evidence relating to medical products and clinical trials, supporting AMA and national regulatory authorities in making informed decisions on product quality, safety and effectiveness.
Their work is expected to strengthen regulatory cooperation across African countries, helping improve access to quality-assured medical products while protecting patients from unsafe, ineffective, substandard and falsified products.
The committees cover seven areas: evaluation of medicines, vaccines and biologicals; clinical trials oversight and good clinical practice; market intelligence and control; quality control laboratories and laboratory networks; vigilance; regulatory inspections; and medical devices, diagnostics and emerging technologies.
Speaking at the inauguration in Kigali on October 26, 2026, AMA Director-General Dr. Delese Mimi Darko described the committees as an important step in building the agency’s scientific capacity.
“With the inauguration of our Technical Committees, we are building an African regulatory institution that belongs to Africa, serves Africa and contributes confidently to the world,” she said.
Darko added that the experts would provide the scientific rigour needed to support regulators across the continent and protect patients who depend on medical products.
Dr. Yossounon Chabi, chairperson of the AMA Governing Board, said the committees would contribute to building a regulatory system that is efficient, transparent and responsive to public health needs.
Their members were selected through an open, competitive and merit-based process following a continent-wide call for expressions of interest. They will serve as individual experts in an independent scientific capacity.
AMA, headquartered in Kigali, aims to strengthen cooperation among national regulatory authorities, allowing countries to share scientific assessments and make regulatory decisions more efficiently. Such cooperation is also expected to help manufacturers navigate regulatory requirements across multiple African markets.
For researchers developing medicines and vaccines, stronger regulatory cooperation could provide earlier scientific guidance, while manufacturers could benefit from clearer regulatory expectations and more predictable routes to market.
The committees form part of wider efforts to build a coordinated continental regulatory system while strengthening national regulatory authorities and regional cooperation.
Two hubs to support regulatory capacity and innovation
The inauguration took place during AMA Week, running from October 25 to 30 in Kigali, which also featured the launch of two hubs designed to strengthen regulatory capacity and support medical product development and manufacturing in Africa.
The Capacity Strengthening Hub will coordinate training, mentoring, peer learning and professional attachments to address gaps in regulatory expertise across the continent.
It will draw on existing African expertise, including national regulatory authorities that have achieved Level 3 maturity under the World Health Organization’s regulatory benchmarking system, as well as Regional Centres of Regulatory Excellence and established regulatory networks.
The second initiative, the Regulatory Innovation and Manufacturing Readiness Hub, will engage innovators and manufacturers earlier in the product development process, helping them understand regulatory requirements and prepare to meet standards for quality, safety and effectiveness.
The hub is also intended to strengthen links between product development and regulatory readiness, supporting efforts to expand Africa’s capacity to develop and manufacture medical products.
Darko said the agency wanted more research, including early-stage clinical trials, to take place in Africa and address the continent’s health needs.
“Africa must also develop products that can serve Africa and compete confidently in the world,” she said.
Rwanda’s State Minister for Health, Dr. Yvan Butera, said the two hubs would help strengthen regulatory institutions and support African manufacturers in bringing quality medical products to market.
“At the heart of healthcare is the simple promise that treatment will help, and that the medicines people receive are safe and of good quality,” he said, adding that protecting public trust required countries to strengthen their regulatory systems and work together.
AMA Director-General Dr. Delese Mimi Darko described the committees as an important step in building the agency’s scientific capacity.The inauguration took place during AMA Week, running from October 25 to 30 in Kigali.The event brought together health officials, medicines regulators, pharmaceutical industry representatives and development partners.
The hubs were launched in Kigali on Tuesday, October 27, during the inaugural AMA Week, held under the theme “Building Africa’s Regulatory Future Together.” The event brought together health officials, medicines regulators, pharmaceutical industry representatives and development partners.
The event brought together health officials, medicines regulators, pharmaceutical industry representatives and development partners.
Rwanda’s Minister of State in the Ministry of Health, Yvan Butera, said the hubs represented progress towards stronger health systems and improved access to safe, quality medical products across Africa.
“At the heart of healthcare is the simple promise that treatment will help, and that the medicines people receive are safe and of good quality,” he said, adding that protecting public trust in medical products required countries to strengthen their regulatory systems and work together.
The first hub, the Capacity Strengthening Hub, will coordinate training, mentoring and professional exchanges to help countries build stronger medicines regulatory systems. It will draw on expertise from African regulatory authorities, universities and regional networks to address skills gaps and strengthen institutions.
The second, the Regulatory Innovation and Manufacturing Readiness Hub, will support pharmaceutical innovators and manufacturers by providing scientific guidance and helping them prepare products to meet regulatory requirements on safety, quality and efficacy.
AMA Director-General Dr Delese Mimi Darko said the hubs would help the agency turn its continental mandate into practical action by bringing together expertise and resources already available across Africa.
“Through this hub, the AMA will engage innovators and manufacturers at earlier stages, support regulatory readiness and help connect product development with the requirements for quality, safety and efficacy,” she said during the launch ceremony at Kigali Marriott Hotel.
AMA Director-General Dr Delese Mimi Darko said the hubs would help the agency turn its continental mandate into practical action.
Darko noted that Africa needed to move beyond being primarily a destination for medical products developed and manufactured elsewhere, arguing that stronger regulatory systems could help local manufacturers expand production and reach wider markets.
She said the agency would build on existing investments in regulatory capacity rather than duplicate work already undertaken by the World Health Organization (WHO), regional economic communities, national authorities and technical partners.
Reducing reliance on imports
The initiative comes as African countries seek to strengthen domestic pharmaceutical production and reduce dependence on imported medicines and vaccines.
Dr Michel Sidibé, the African Union Special Envoy for the AMA, said Africa continued to rely heavily on imports, estimating that the continent imported more than 70% of its medicines and 99% of its vaccines.
He argued that fragmented regulatory systems remained an obstacle to pharmaceutical investment and the expansion of locally manufactured products across African markets.
Dr Michel Sidibé, the African Union Special Envoy for the AMA, said Africa continued to rely heavily on imports.
Without stronger coordination, manufacturers face the challenge of navigating different national regulatory requirements before selling the same product in multiple countries.
Sidibé said the AMA could help address this challenge by enabling countries to share scientific assessments and reduce duplication in product evaluations.
He added that a medicine manufactured in Kigali should eventually be able to reach other African markets more quickly through stronger regulatory cooperation.
The agency’s work is also expected to support the development of African pharmaceutical research, clinical trials and products addressing the continent’s health needs.
Professor Paul S. Lalvani, founder and executive director of Empower School of Health, said building local manufacturing capacity required investment not only in facilities but also in the skilled workforce and institutions needed to operate them.
He said the AMA’s hubs could help countries share successful approaches to training and regulatory development, drawing on existing institutions and expertise.
Lalvani argued that Africa’s progress in pharmaceutical manufacturing should be measured by its ability to produce more of the medicines, vaccines, medical devices and diagnostics its populations need.
Professor Paul S. Lalvani, founder and executive director of Empower School of Health, said Africa needs skilled workers and strong institutions alongside investment in pharmaceutical manufacturing.
Strengthening continental cooperation
The hubs form part of the AMA’s broader effort to establish a more coordinated system for regulating medical products across Africa.
According to Darko, the agency is developing networks to improve cooperation among national regulatory authorities, quality-control laboratories and other institutions involved in assessing the safety and quality of medical products.
These include AfriVigilance and a planned Regulatory Rapid Alerts and Information Network, which are intended to strengthen the sharing of safety information and improve responses to substandard and falsified medicines.
The agency is also working with national regulators, regional economic communities, the WHO, the African Union Development Agency-NEPAD and the African Continental Free Trade Area Secretariat.
WHO Director-General Dr Tedros Adhanom Ghebreyesus said fragmented regulatory systems could delay access to medicines, increase costs and weaken health security.
Tedros reaffirmed the WHO’s commitment to supporting the AMA and national regulatory authorities through technical and financial assistance.
Dr. Tedros Adhanom Ghebreyesus, Director-General of the World Health Organization (WHO), delivered a recorded address to delegates at AMA Week.
He said 10 national regulatory authorities in Africa had reached Level 3 maturity under the WHO’s Global Benchmarking Tool: Egypt, Ethiopia, Ghana, Mozambique, Nigeria, Rwanda, Senegal, South Africa, Tanzania and Zimbabwe. The achievement provides a foundation for greater regulatory cooperation across the continent.
Tedros also called on African Union member states that had not ratified the AMA Treaty to do so and urged governments and partners to provide sustained political and financial support to the agency.
The AMA is headquartered in Kigali, where Rwanda has supported its establishment and operations since 2023, when the government signed a host agreement with the African Union. The agency became operational in October 2025.
The agency’s longer-term ambition is to help African countries strengthen national regulatory systems while enabling greater cooperation across borders, improving access to quality-assured medical products and supporting the growth of the continent’s pharmaceutical industry.
The hubs were launched in Kigali on Tuesday, October 27, during the inaugural AMA Week, held under the theme “Building Africa’s Regulatory Future Together.” The event brought together health officials, medicines regulators, pharmaceutical industry representatives and development partners.